Q050A myth: Ontario has no two-visit or dx 428 rule
A common belief says you can bill Q050A, the $125 heart failure management incentive, only after two rostered visits with diagnostic code 428. Ontario has no such rule. It's the rule for British Columbia's fee 14051, a $125 heart failure incentive with an almost identical name.
Ontario vs British Columbia
| Ontario Q050A | British Columbia 14051 | |
|---|---|---|
| Fee | $125 a year | $125 a year |
| Two visits first | Not required | Required, in the past 12 months |
| Diagnostic code 428 | Not required | Required on the claim |
| What it pays for | A complete heart failure flow sheet | Guideline care in the past year |
| How often | Once per 365 days | Once per 12 months |
What Ontario's Schedule says
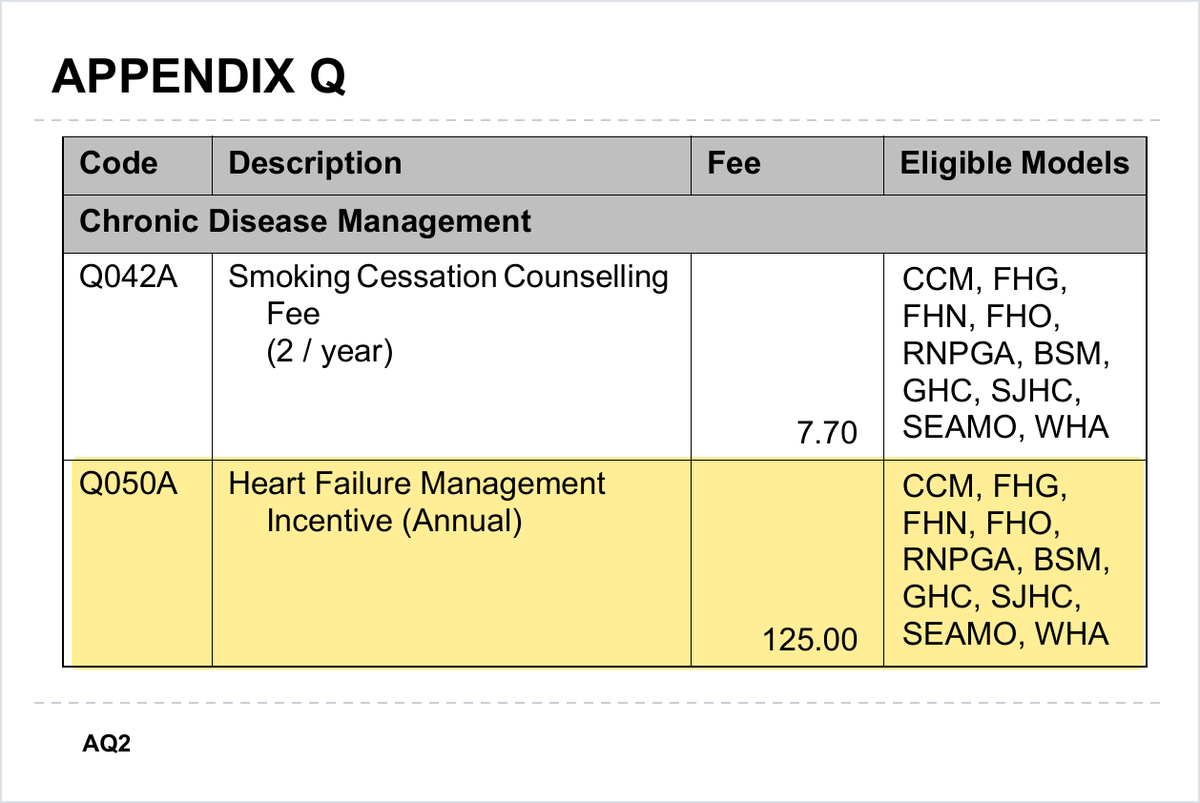
Where "two visits" started

The sentence describes how long finishing the flow sheet usually takes. It isn't a condition, and the fact sheet names no diagnostic code.
Where "must" and "428" come from

What Q050A needs in Ontario
- A heart failure patient enrolled with you. Q050A is for enrolment models only (Schedule of Benefits, AQ2).
- A complete flow sheet in the chart that tracks a full physical exam; Na+, K+, serum creatinine and eGFR; education on risk factors and self-management; and first-line, symptom-relief and preventive medications (OMA Q-codes guide p.13).
- Bill it once per 365 days, on its own or with a visit (Ministry fact sheet, April 2008).
Should I still put 428 on the claim?
Yes. 428 is the diagnostic code for congestive heart failure, so it's the natural code to use. It just isn't a published condition for Q050A.
Can I bill Q050A after a single visit?
Yes, if every flow sheet element is documented. Most patients need more than one visit before labs are back and medications reviewed, so two visits is common in practice (Ministry fact sheet, April 2008).
Where does Ontario require 428?
On specialist premiums, not Q050A. The chronic disease assessment premium E078 lists 428 among the diagnostic codes that must accompany the claim (Schedule of Benefits, GP26).
Related
- Q050A heart failure management incentive
- OHIP billing code for diabetes management: K030A, Q040A and K029A
- OHIP billing code for smoking cessation: E079A, K039A and Q042A
- Diagnostic code 428: congestive heart failure
Sources
Schedule of Benefits: Physician Services (July 1, 2026), Appendix Q, AQ2
Ministry of Health and Long-Term Care: Heart Failure Management Incentive fact sheet (April 2008)
OMA: Primary Care Q-Codes Quick Reference Guide
OHIP INFOBulletins 2026 and 2025
British Columbia Medical Services Plan: Chronic Disease Management fees 14050 to 14053
APEX offers every physician or group a unique, transparent overview over their billing records.